
How Integrated LIS & RCM Systems Improve Lab Profitability
A lab doesn’t really get paid when a result is released. It gets paid when a clean claim reaches the right payer, passes their edits, and the money lands in your account. Everything between those two moments is where margins quietly disappear.
That gap is exactly what integrated LIS and RCM systems are built to close. When your laboratory information system (LIS) and your revenue cycle management (RCM) platform share data automatically, billing starts from verified, complete information instead of a pile of re-typed fields. The result is fewer denials, faster payments, lower admin cost, and a clearer picture of which parts of your lab actually make money.
In this guide, you’ll learn how the integration works, where disconnected systems leak revenue, the specific ways integration lifts lab profitability, and how to evaluate and roll out an integrated platform without disrupting operations.
Quick Answer: How Does Integrated LIS and RCM Improve Lab Profitability?
Integrated LIS and RCM systems improve lab profitability by sending order, test, diagnosis and patient data straight from the LIS into the billing workflow. This produces cleaner claims, cuts denials, shortens days in accounts receivable, reduces manual work, and gives lab leaders real-time financial visibility by test, payer and client.
Key Takeaways
- Cleaner claims: data captured once at order entry flows into billing without re-keying.
- Fewer denials: payer rules and medical necessity checks run before submission, not after rejection.
- Faster cash: billing triggers fire when results are finalized, not when someone remembers.
- Lower cost to collect: less rework means smaller teams can handle more volume.
- Better decisions: test-level and payer-level margin data replaces guesswork.
- Lower compliance risk: one audit trail from order to payment.
What Is LIS and RCM Integration?
Two systems sit at the heart of every lab’s operation, and they speak very different languages.
The LIS: Your Operational Engine
A laboratory information system manages test ordering, specimen accessioning and tracking, instrument results, quality control, and result reporting. It knows what was ordered, what was actually performed, and when it was verified.
The RCM Platform: Your Financial Engine
Laboratory revenue cycle management covers everything after the test: charge capture, coding, eligibility checks, claim creation, submission, payment posting, denial management and patient or client billing.
What “Integrated” Actually Means
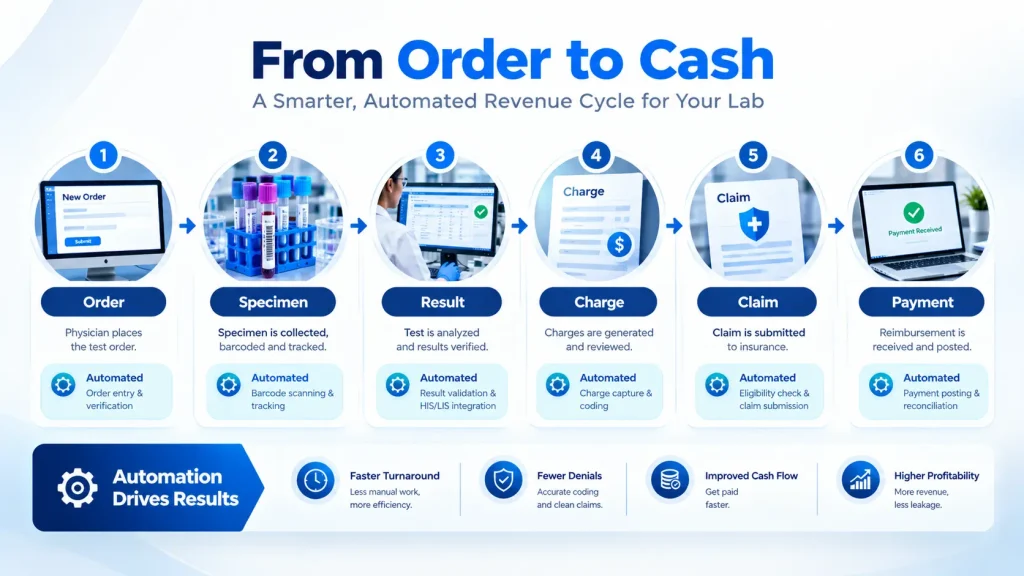
Integration means these two engines share a live data connection. A test finalized in the LIS becomes a billable charge in the RCM without anyone exporting a spreadsheet. A denial in the RCM can point back to the exact order and requisition in the LIS. Both teams look at the same record.
Three Common Integration Models
- Native, all-in-one platform: LIS and RCM are built on one database. Fewest moving parts.
- Interface-based integration: two separate products exchange data through HL7, APIs or flat files. Works, but needs monitoring.
- Batch file transfer: data moves on a schedule. Better than re-typing, but it still creates delays and timing gaps.
Where Disconnected Systems Quietly Drain Your Margins
Labs rarely notice revenue leakage as a single big event. It shows up as a hundred small frictions: a missing ICD-10 code here, a transposed insurance ID there, a charge that never made it across. Add them up and the number gets uncomfortable.
The Most Common Leak Points
- Manual re-entry: every handoff is a chance for a typo in demographics, policy numbers or provider identifiers.
- Test-to-code mismatches: what was performed doesn’t match the CPT code that gets billed.
- Missed charges: reflex tests, add-ons and repeats don’t always make it into billing.
- Missing medical necessity: no diagnosis, or a diagnosis that doesn’t support the test, is one of the most common reasons labs get denied.
- Billing lag: claims wait for someone to manually release them, stretching the revenue cycle.
- Timely filing misses: payers set deadlines, and Medicare, for example, generally expects claims within 12 months of the date of service. Late claims are often unrecoverable.
- Unworked denials: without clear links back to the original order, appeals take longer and many never get filed.
- Blind spots: finance sees payments, operations sees volume, and nobody sees margin per test.
Disconnected vs. Integrated: A Side-by-Side View
| Workflow Area | Disconnected LIS + Billing | Integrated LIS + RCM |
|---|---|---|
| Data entry | Entered in the LIS, then re-keyed or imported into billing | Captured once at order entry and reused |
| Charge capture | Manual or batch; reflex and add-on tests are easy to miss | Automatic from finalized test events |
| Claim timing | Depends on staff releasing batches | Triggered by result verification or release |
| Error detection | After payer rejection or denial | Before submission, through pre-billing checks |
| Denial research | Searching across two systems | One click from claim back to order and result |
| Reporting | Exports and spreadsheets, often out of date | Live dashboards by test, payer, provider and client |
| Audit trail | Split across systems with gaps | Continuous, timestamped, order to payment |
7 Ways Integrated LIS and RCM Systems Improve Lab Profitability
1. Cleaner Claims and a Higher First-Pass Acceptance Rate
The cheapest claim to process is the one that’s right the first time. When patient demographics, ordering provider details, test codes and diagnosis information come directly from the LIS, there’s far less opportunity for the small errors that trigger rejections.
Many revenue cycle teams use a clean claim rate of roughly 95% or higher as a working benchmark. Whether you hit it depends heavily on how much of your data is typed more than once.
What This Means for Your Bottom Line
- Fewer claims bounced back for correction
- Shorter days in A/R
- Less staff time spent on rework
- More predictable monthly cash flow
2. Fewer Denials Through Pre-Billing Payer Rules
A payer rules engine is only as smart as the data you feed it. In a disconnected setup, the rules fire late, after the claim is built, or they never see the full order context.
With integration, the system can check each claim against payer-specific requirements before it leaves your building. Typical checks include:
- Does the diagnosis code support medical necessity for this test under the payer’s policy?
- Is a prior authorization required, and is it on file?
- Are there frequency limits or bundling edits, such as NCCI edits, that apply?
- Is the patient’s coverage active on the date of service?
Catching a problem at the front end costs minutes. Catching it after a denial costs days, and sometimes the claim itself.
3. Real-Time Billing Triggers Shorten the Revenue Cycle
In many labs, billing begins when someone has time to start it. Integration changes that by letting the LIS release a charge the moment a defined event occurs, such as specimen receipt, result verification or report release.
That unlocks a cascade of benefits:
- Charges are created without delay, which reduces charge lag
- Eligibility checks (270/271 transactions) can run early
- Billing exceptions are flagged while the specimen is still fresh in everyone’s mind
- Claims (typically 837P files) go out sooner, and remittances (835 ERAs) come back to a system that already knows the context
4. Test-Level and Payer-Level Financial Visibility
Most lab owners can tell you revenue by month. Far fewer can tell you which tests deliver healthy margins, which payers consistently pay late, or which referring clients generate the most rejections.
Because integrated platforms connect operational data (volume, turnaround time, reagent use) with financial data (allowed amounts, payments, adjustments), they can answer questions like:
- Which tests are most profitable after cost of goods and collection effort?
- Which payers are slowest, and which deny most often?
- Which ordering clients send incomplete requisitions that cost us money?
- Where do we lose the most revenue between billed and collected?
That insight turns contract negotiations, test menu decisions and sales priorities into evidence-based choices.
5. Lower Administrative Overhead and Cost to Collect
Every hour spent reconciling two systems is an hour not spent working denials or resolving payer issues. Integration reduces that load by removing duplicate entry, auto-matching claims to test events and simplifying appeals.
The practical outcome is that a lean billing team can handle more volume without adding headcount. For a growing lab, that’s often the difference between scaling smoothly and hiring ahead of revenue.
6. Stronger Compliance and Lower Audit Exposure
Profitability isn’t only about earning revenue. It’s about keeping it. A claim that gets paid and later clawed back after an audit isn’t revenue; it’s a loan.
Integrated platforms support compliance by:
- Maintaining a continuous chain of custody from order to invoice
- Creating timestamped audit logs for every billed test
- Keeping documentation (requisitions, medical necessity, results) tied to the claim
- Applying consistent access controls and encryption across the workflow, which supports HIPAA requirements and CLIA expectations
If you’d like to go deeper on the security side, see our overview of HIPAA-compliant LIS data security.
7. A Financial Foundation That Scales
Adding a new client, a new payer contract or a new test line is exciting until your billing process buckles under it. Integrated workflows are rules-driven, so new volume follows the same logic as old volume. That makes growth far less risky.
Why Reimbursement Pressure Makes Integration More Urgent
Lab margins are getting squeezed from outside as well as inside. Under the Protecting Access to Medicare Act (PAMA), Medicare Clinical Laboratory Fee Schedule (CLFS) rates are based on private payor data reported by applicable laboratories. According to the Association for Diagnostics & Laboratory Medicine (ADLM), Congress delayed scheduled CLFS reductions through 2026, and the 2026 reporting window closed on July 31, with data from January 1 through June 30, 2025 being used to set rates beginning in 2027. Under current law, reductions of up to 15% per year could resume in 2027 and run through 2029, and the RESULTS Act, which would change how the data is collected, is still being pushed in Congress.
Policy can change quickly, so check the latest guidance on the CMS CLFS reporting page before making financial plans. The point for your lab is simple: when reimbursement per test may fall, every avoidable denial, write-off and hour of rework matters more. Integrated systems also make it easier to see exactly which tests, payers and contracts are most exposed.
What Does the Business Case Look Like? A Simple Illustration
Every lab is different, so treat the numbers below as a hypothetical model, not a promise. Use your own data to run the same math.
| Metric (hypothetical lab) | Before Integration | After Integration |
|---|---|---|
| Monthly billed claims | 10,000 | 10,000 |
| First-pass acceptance | 85% | 95% |
| Claims needing rework each month | 1,500 | 500 |
| Rework cost per claim (staff time) | $25 | $25 |
| Monthly rework cost | $37,500 | $12,500 |
In this example, labor savings alone are about $25,000 a month, before counting faster payments, recovered denials, or avoided write-offs. The point isn’t the specific figure. It’s that small improvements in first-pass acceptance compound across thousands of claims.
Metrics to Track Before and After
- Clean claim rate / first-pass acceptance rate
- Denial rate, broken down by reason code and payer
- Days in A/R and aging buckets (30/60/90+)
- Net collection rate
- Charge lag (time from result to charge creation)
- Cost to collect per claim
- Revenue per test and margin by payer
How to Evaluate an Integrated LIS and RCM Solution
Not every platform that says “integrated” delivers the same experience. Use this checklist when you talk to vendors.
Questions Worth Asking
- Is the integration native or interface-based? If it’s an interface, who monitors it, and what happens when it fails?
- Can it trigger billing from real events? Ask about specimen receipt, verification and release triggers.
- How are payer rules built and maintained? Static lists go stale fast; you want rules that are regularly updated and editable.
- How does it handle reflex testing, add-ons and repeats? These are classic leakage points.
- What does denial management look like? Look for reason-code analytics and a direct link back to the order.
- Can you see profitability by test, payer, provider and client? Ask to see a live dashboard, not a slide.
- How does it connect with EHRs, analyzers and portals? Standards like HL7 matter. See our guide to LIS integrations with EHR, EMR and analyzers.
- What compliance features are built in? Audit logs, role-based access, encryption and documentation retention.
- Is it built for your lab type? Toxicology, pathology, reference and physician office labs each have distinct billing needs.
- What does implementation and support look like? Data migration, training and responsive support matter as much as features.
How Prolis Approaches Integrated LIS and RCM
Prolis offers an integrated LIS-RCM platform designed to carry a test from order to payment in a single workflow. It’s built to help labs:
- Reduce manual billing tasks
- Embed payer rule logic directly into lab workflows
- Improve first-pass claim acceptance
- See financial performance in real time
- Align operational metrics, such as turnaround time and volume, with revenue results
Whether you run a startup toxicology lab or a high-volume clinical lab, the goal is the same: fewer handoffs, fewer surprises, and more of what you bill actually collected. You can explore how it works on the Lab RCM page.
A Practical Roadmap for Rolling Out Integration
Step 1: Baseline Your Current Performance
Pull 6 to 12 months of data: denial rate by reason, days in A/R, charge lag, write-offs and rework hours. You can’t prove improvement without a starting line.
Step 2: Map Your Real Workflow
Walk an order from requisition to payment and mark every manual touch. Those touches are your priority list.
Step 3: Clean Your Master Data
Test catalog, CPT mappings, payer tables and fee schedules need to be accurate before they go into any new system. Bad data migrates just as easily as good data.
Step 4: Configure Triggers and Payer Rules
Decide when charges release, which checks must pass, and which exceptions need human review.
Step 5: Pilot, Then Expand
Start with one payer group, one client set or one department. Compare results against your baseline, fix issues and then widen the rollout.
Step 6: Train Both Sides Together
Lab operations and billing staff should learn the new workflow together. Many billing problems start with a requisition field that nobody in the lab knew mattered.
Step 7: Review KPIs Every Month
Treat integration as the beginning of an optimization cycle. Look at denial trends, adjust rules and keep refining.
Common Mistakes to Avoid
- Treating it as purely an IT project. It’s a revenue strategy; finance and operations need seats at the table.
- Skipping data cleanup. Automation speeds up errors as well as accuracy.
- Over-customizing on day one. Start with proven workflows and tune from there.
- Ignoring front-end data capture. Integration can’t fix a requisition that arrives without a diagnosis code. Train clients and ordering providers too.
- Not monitoring interfaces. If your setup depends on interfaces, set up alerts for failed messages.
- Forgetting to measure. Without KPIs, you won’t know what’s working.
Final Thoughts: Integration Is a Profitability Strategy, Not Just an IT Upgrade
Labs that thrive in the current environment tend to share one trait: their operations and billing teams are working from the same facts. Integrating your LIS and RCM won’t remove every denial or reimbursement challenge, but it removes the avoidable ones, and in a margin-sensitive business, avoidable losses are the easiest to win back.
If your team is still re-keying data, chasing missing diagnosis codes, or guessing which tests are profitable, it may be time to see what a connected workflow looks like in practice.
Ready to see it in action? Book a Prolis demo and we’ll walk you through how an integrated LIS and RCM platform can fit your lab’s workflow, payer mix and growth plans.
Frequently Asked Questions About Integrated LIS and RCM
What is an integrated LIS and RCM system?
An integrated LIS and RCM system connects the laboratory information system, which manages orders, specimens and results, with the revenue cycle management platform, which handles claims, payer rules, denials and collections. Data flows between the two automatically, so billing starts from verified lab data instead of manual re-entry.
How does LIS and RCM integration improve lab profitability?
It improves profitability by producing cleaner claims, reducing denials, shortening days in accounts receivable, cutting administrative labor, and showing which tests, payers and clients earn the most. It also lowers compliance risk, which protects revenue from audits and clawbacks.
What causes revenue leakage in clinical laboratories?
Common causes include missed charges, wrong or missing CPT and ICD-10 codes, incomplete demographics or insurance details, absent medical necessity documentation, late claim submission and unworked denials. Most of these begin where the LIS and the billing system fail to share data.
Is an all-in-one LIS with built-in RCM better than two separate systems?
For most labs, yes. A single platform removes interface maintenance and data mismatches. A well-built interface between two best-of-breed systems can work, but it needs careful testing, active monitoring and a clear owner when something breaks.
How long does it take to see ROI from LIS-RCM integration?
It varies by lab size and starting point. Many labs notice early gains in claim accuracy and billing speed within the first few months, while the full effect on denials and A/R typically becomes clear over two to four billing cycles.
What KPIs should labs track after integrating LIS and RCM?
Track clean claim rate, first-pass acceptance, denial rate by reason code, days in A/R, net collection rate, cost to collect, charge lag and revenue per test by payer.
Can integration help with PAMA and Medicare reimbursement changes?
Indirectly, yes. Integrated systems give you accurate payer-level payment data and test-level margins, which supports correct private payor reporting and helps you model the impact of potential Clinical Laboratory Fee Schedule changes.
Which types of labs benefit most from integrated LIS and RCM?
Any lab that bills payers benefits, but the effect is especially strong for high-volume clinical labs, toxicology labs with complex medical necessity rules, reference labs managing many client accounts, and growing labs that can’t afford billing bottlenecks.


